

Hair Transplant Turkey: Surgical Techniques, Clinic Vetting, and Regrowth Timelines
Compare FUE and DHI hair transplant techniques in Turkey, understand clinic safety standards, average costs, and the clinical 12-month regrowth timeline.

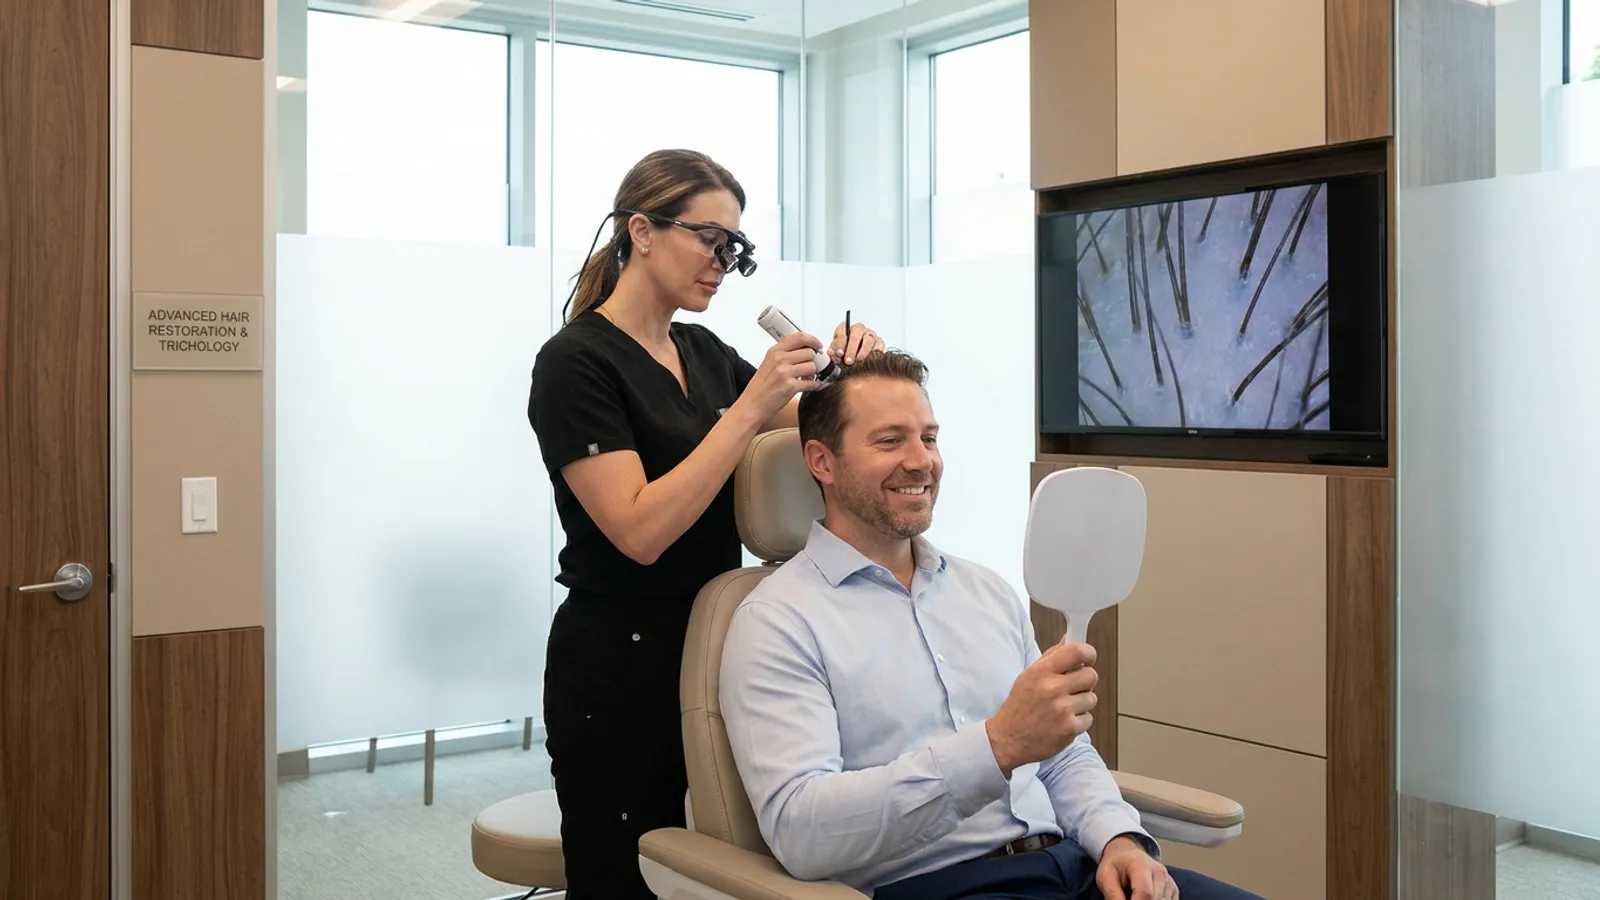
Hair Transplant Turkey: Surgical Techniques, Clinic Vetting, and Regrowth Timelines
Quick Answer: A successful hair restoration procedure in Turkey depends on accurate donor evaluation, realistic graft limits (3,000-4,000 per session), and direct oversight by a licensed medical doctor rather than unsupervised technicians.
Key Takeaways:
- FUE, sapphire FUE, and DHI offer distinct advantages depending on targeted hair density, graft volume, and whether recipient-site shaving is feasible.
- Safe single-session harvesting rarely exceeds 4,000 grafts; higher numbers significantly elevate the risk of donor depletion, transection, and scarring.
- The Turkish Ministry of Health mandates that surgical planning, incision channel creation, and medical oversight be performed by licensed physicians.
- Post-operative shedding occurs within the first eight weeks, with visible cosmetic growth emerging around month four and final density settling between nine and twelve months.
- Comprehensive clinic packages must itemize surgeon involvement, local anesthesia protocols, translation services, and 12 months of structured remote follow-up.
Hair transplantation is an outpatient surgical procedure that relocates healthy, androgen-resistant follicular units from the occipital scalp (donor zone) to thinning or balding areas (recipient zone). International patients travel for a hair transplant in Turkey due to concentrated surgical expertise, comprehensive care packages, and well-developed medical tourism infrastructure. Making an informed decision requires evaluating biological candidacy, comparing extraction and implantation methodologies, confirming clinic licensing standards, and maintaining realistic expectations regarding post-operative healing.
Candidacy Criteria: Assessing Donor Density and Pattern Stability
A suitable candidate for a hair transplant in Turkey presents with stabilised hair loss and an adequate, healthy donor zone located on the occipital scalp. Patients experiencing active, untreated shedding or conditions such as diffuse unpatterned alopecia (DUPA) generally require medical stabilisation prior to surgical consideration.
Evaluating candidacy begins with an objective assessment of hair loss progression. Clinicians use the Norwood Scale for male pattern hair loss (androgenetic alopecia) or the Ludwig Scale for female pattern hair loss. Individuals presenting between Norwood Stages II and V typically make the strongest surgical candidates. At these stages, hair loss patterns have declared themselves. The surrounding donor area also remains robust enough to yield significant coverage without depleting reserve follicles.
Key biological factors evaluated during pre-operative trichological screening include:
- Donor Hair Density: A donor area should ideally supply at least 65 to 80 follicular units per square centimetre. Patients with low baseline density risk visible thinning in the extraction zone if excessive harvesting occurs.
- Hair Shaft Caliber: Coarse or wavy hair provides substantially greater visual scalp coverage than fine, straight hair at identical graft counts, influencing the total volume required.
- Pattern Stability: Surgical intervention works best when hair loss has slowed. Young patients under age 25 often experience rapid, unpredictable recession. Operating prematurely can leave isolated islands of transplanted hair as native hair behind them continues to shed.
- Scalp Health: The recipient tissue must be free from active inflammatory dermatoses, including severe seborrheic dermatitis, psoriasis, or lichen planopilaris.
- Underlying Medical Conditions: Systemic disorders such as poorly controlled diabetes mellitus or active autoimmune conditions impair microvascular wound healing and graft survival.
Patients with active shedding typically benefit from first-line medical therapy, such as oral or topical minoxidil and 5-alpha reductase inhibitors like finasteride, for 6 to 12 months before scheduling surgery. Medical therapy stabilises miniaturising follicles, preserves native coverage, and clarifies the true boundary of the surgical recipient site.
Comparing Surgical Techniques: FUE Hair Transplant Turkey vs Sapphire FUE and DHI
Standard Follicular Unit Extraction (FUE) isolates individual follicular units using micro-punches, sapphire FUE uses V-shaped sapphire blades for pre-made incisions to achieve closer graft placement, and Direct Hair Implantation (DHI) employs a specialized implanter pen to open recipient sites and place follicles concurrently. Each method provides high graft survival rates when matched appropriately to the patient's scalp laxity and targeted density.
Follicular extraction techniques have largely replaced follicular unit transplantation (FUT or strip surgery), eliminating the linear donor scar. In modern practices, manual or micro-motor punches ranging from 0.7 mm to 0.9 mm in diameter isolate intact follicular groupings (containing one to four hairs each) while minimising surrounding epidermal trauma.
During a standard fue hair transplant turkey, recipient sites are created using surgical steel blades, followed by manual placement of grafts with fine forceps. This method remains widely used for extensive balding areas where large graft numbers (3,000 or more) are required across broad surface areas.
Sapphire FUE refines this process by substituting steel blades with blades crafted from synthetic sapphire crystal. Because sapphire blades maintain a sharper, smoother edge, they generate micro-incisions with reduced tissue tearing. The resulting V-shaped incisions allow surgeons to create channels closer together, supporting recipient densities of 40 to 50 grafts per square centimetre while generating smaller scabs during recovery.
Direct Hair Implantation, commonly referred to as a dhi hair transplant turkey, relies on mechanical implanter pens (such as the Choi Implanter). In this approach, technicians load harvested follicular units into hollow needles within the pen. The operating doctor then pierces the recipient scalp and deposits the graft in a single motion. DHI eliminates the pre-incision phase, protects grafts from prolonged ambient exposure, and allows precise control over insertion angle, depth, and direction. It is frequently recommended for frontal hairline reconstruction, temple refinement, or densifying areas between native hairs without shaving the entire head.
| Feature | Standard FUE | Sapphire FUE | DHI (Direct Hair Implantation) |
|---|---|---|---|
| Incision Tool | Surgical steel micro-blade | V-shaped synthetic sapphire blade | Choi implanter pen (hollow needle) |
| Recipient Channel Creation | Separate step before placement | Separate step before placement | Simultaneous channel opening and graft placement |
| Typical Target Density | 30-40 grafts/cm² | 40-50 grafts/cm² | 45-55+ grafts/cm² |
| Graft Handling Time | Standard | Standard | Minimal (loaded into pen and placed directly) |
| Recipient Shaving | Complete shaving usually required | Complete shaving usually required | Unshaven recipient options frequently possible |
| Best Clinical Indication | Norwood IV, VI large surface coverage | Norwood III, V high-density restoration | Hairline refinement, crown filling, unshaven procedures |
| Session Duration | 5-7 hours | 6-8 hours | 6-8 hours (limited graft volumes per session) |
Vetting Hair Transplant Clinics in Turkey: Licensing, Staffing, and Red Flags
Evaluating hair transplant clinics in Turkey requires verifying that the surgical facility holds a clinical license issued by the Turkish Ministry of Health and ensuring a medical doctor directly plans the hairline, makes incisions, and oversees the surgical team. Warning signs include promises of unlimited graft numbers exceeding 5,000 grafts in a single sitting, lack of named medical practitioners, and non-transparent revision policies.
Turkey hosts hundreds of hair restoration providers, ranging from surgical departments in full-scale hospitals to low-cost, technician-driven facilities often termed "hair mills." High-volume commercial centres frequently book dozens of patients per day, relying entirely on non-medical assistants with minimal clinical training to conduct invasive surgical steps.
To identify reputable hair transplant clinics in turkey, verify the following institutional criteria:
- Statutory Licensing: Confirm that the facility is registered with the Turkish Ministry of Health (T.C. Sağlık Bakanlığı) as a licensed medical centre, polyclinic, or general hospital. Aesthetic surgeries cannot legally take place in unlicensed salon suites or standard office buildings.
- Physician Identification: Legitimate clinics identify the primary operating medical doctor by name, medical registration number, and professional qualifications before booking. Verify whether the practitioner holds active membership in recognized international scientific bodies, such as the International Society of Hair Restoration Surgery (ISHRS).
- Dedicated Daily Caseloads: Quality-oriented clinics typically limit intake to one or two surgical patients per operating team per day. This limitation ensures the doctor remains physically present throughout critical phases rather than circulating through multiple operating rooms.
- Transparent Communication Channels: Reputable facilities provide pre-operative medical assessments directly from clinical staff, rather than using non-medical sales agents who rely on aggressive sales tactics or downplay biological constraints.
- Clear Revision and Complication Policies: The clinic's documentation must articulate protocols regarding graft survival evaluation at the 12-month mark, corrective options if growth goals are unmet, and management plans for immediate post-operative complications.
Be cautious of providers advertising "guaranteed 100% graft survival," "unlimited graft sessions," or proprietary techniques that lack peer-reviewed medical validation. Hair restoration is a biological intervention with inherent physiological limits, and reputable clinicians frame outcomes around measured clinical probabilities.
The Role of Certified Hair Transplant Surgeons Turkey in Extraction and Implantation
Hair restoration outcomes depend on surgical oversight, where licensed medical doctors determine extraction patterns to preserve donor reserves and control the precise angle and depth of recipient channels. Although trained surgical technicians assist with graft handling and sorting under direct supervision, unregulated facilities delegating the entire procedure to unsupervised technicians present elevated risks of poor angulation, unnatural hairlines, and donor overharvesting.
In a compliant surgical workflow, responsibilities are clearly demarcated between the licensed doctor and qualified surgical assistants. Reputable hair transplant surgeons turkey maintain direct ownership of the following critical interventions:
- Pre-Operative Design and Hairline Planning: The physician designs the hairline, accounting for facial symmetry, bone structure, age-appropriate recession, and long-term hair loss progression.
- Administration of Local Anaesthesia: Subcutaneous infiltration of local anaesthetics (such as lidocaine combined with adrenaline to induce vasoconstriction and haemostasis) requires medical monitoring to avoid toxicity, severe hypotension, or systemic cardiovascular distress.
- Harvest Pattern Strategy: The doctor determines the micro-punch extraction pattern across the safe donor zone, calculating spacing to avoid a moth-eaten appearance or localized bald spots.
- Recipient Channel Incisions: Creating recipient sites dictates growth direction, angle of emergence (typically 10 to 15 degrees at the immediate hairline, widening to 30 to 45 degrees further back), and distribution density. Misaligned channels result in erratic, unmanageable hair growth.
Trained surgical technicians provide critical support by extracting pre-cored grafts, carefully sorting follicular units under stereomicroscopes into single-, double-, and multi-hair groupings, and keeping tissue chilled in specialized holding solutions (such as chilled saline, Ringer's lactate, or HypoThermosol with ATP). When clinics delegate surgical incisions or core extractions entirely to unsupervised assistants, patients face higher rates of transected roots, misangled hair growth, and irreversible donor depletion.
Understanding Realistic Graft Capacities and Safe Donor Management
A safe single-session graft harvesting limit generally ranges between 3,000 and 4,000 follicular units to protect the patient's donor reserve from irreversible thinning and patchy scarring. Exceeding this physiological threshold in one session risks follicular transection and compromises donor density required for prospective future touch-ups.
The human donor zone on the occipital and parietal scalp contains a finite supply of terminal hairs. An average Caucasian donor area, for instance, contains roughly 6,000 to 8,000 harvestable follicular units across an individual's lifetime. Extracting too many units in a single intervention exhausts these reserves, leaving the back of the head visibly bare and ruling out future corrective surgeries if hair loss progresses.
Key benchmarks for donor capacity management include:
- Total Lifetime Donor Reserve: Approximately 6,000 to 8,000 harvestable follicular units across the occipital and parietal scalp.
- First Procedure Safe Limit: 3,000 to 3,500 grafts per single session.
- Preserved Reserve: 2,500 to 4,000 grafts held in reserve for future progressive loss.
- Mega-Session Overharvesting Risk (>5,000 Grafts): Severe donor depletion, visible moth-eaten thinning, and fibrotic micro-scarring.
Safe donor management follows mathematical extraction ratios:
- Harvesting Ratios: Surgeons typically harvest no more than one out of every four to five follicular units within a given square centimetre (an extraction density of 15 to 20 grafts/cm²). This maintains enough adjacent native hair to conceal micro-scars.
- Safe Donor Area Boundaries: Follicles must be harvested exclusively from the androgen-resistant safe donor zone, the scalp area least susceptible to dihydrotestosterone (DHT). Harvesting too high toward the crown or too low toward the nape risks taking hairs that are genetically programmed to thin over time.
- Follicular Transection Rates: High-speed, aggressive harvesting by unvetted operators often elevates the transection rate (severing the hair bulb below the skin surface) above 10% to 15%, destroying donor follicles without yielding viable grafts. In qualified hands, transection rates remain consistently under 3% to 5%.
- Staged Surgical Approaches: Patients presenting with advanced balding (Norwood V and VI) who require 5,000 to 6,000 total grafts achieve safer, more natural outcomes by dividing the process into two separate sessions spaced 10 to 12 months apart. Staging the intervention allows the donor scalp microcirculation to recover and prevents vascular compromise in the recipient bed.
Recovery Schedule and Results Timeline: What to Expect Across 12 Months
Shedding of transplanted hairs (shock loss) typically begins between weeks two and eight post-procedure, followed by initial fine regrowth around month three to four, with matured density and natural texture settling between nine and twelve months. Patients receive post-operative washing protocols and can safely undertake return commercial flights within 48 to 72 hours after attending an in-clinic medical wash and donor evaluation.
The biological cycle of hair restoration requires patience, as transplanted follicles undergo a dormant phase before entering active anagen growth. The recovery follows a structured sequence:
- Days 1-3: Scalp swelling, crust formation, and initial clinic wash.
- Days 4-10: Daily gentle washing, leading to complete scab detachment by day 10.
- Weeks 2-8: Shock loss phase, where transplanted hair shafts shed while roots remain dormant under the skin.
- Months 3-4: Early emergence of fine, lightly pigmented hairs.
- Months 6-8: Hair shaft thickening, reaching approximately 50% to 60% of expected visual density.
- Months 9-12: Maturation of hair calibre, texture integration, and establishment of final cosmetic density.
Immediate Post-Operative Period (Days 1 to 10)
Patients leave surgery wearing a light bandage on the donor area, leaving the recipient area exposed to ambient air to dry. Local anesthetic fluids mixed with saline cause mild forehead and periorbital swelling (edema), which migrates downward before resolving naturally by day four or five. Sleeping semi-upright at a 45-degree angle on a neck pillow prevents direct friction against newly planted grafts.
On day two or three, patients return to the clinic for their initial medical wash. Staff demonstrate how to apply a moisturising panthenol lotion to soften epidermal scabs, followed by gentle tapping with a diluted, pH-balanced shampoo. Rubbing, scratching, or exposing the recipient zone to high-pressure shower heads must be avoided. By day 10, gentle circular washing safely dislodges all remaining scabs. At this point, the grafts are anchored within the scalp dermis.
Shock Loss Phase (Weeks 2 to 8)
Between the second and eighth week, up to 80% to 90% of transplanted hair shafts shed. Known clinically as telogen effluvium, this temporary response occurs as surgical trauma pushes follicles into a brief resting phase. The dermal papilla and stem cells remain anchored under the skin; only the outer hair shaft detaches. Native hairs adjacent to the recipient or donor sites may also temporarily thin, but they regrow as the scalp stabilises.
Early Regrowth to Maturation (Months 3 to 12)
- Months 3 to 4: Follicles re-enter the anagen (growth) phase. Initial regrowth appears as fine, lightly pigmented hairs that resemble peach fuzz. Temporary, mild folliculitis (small pimple-like bumps) may develop as newly growing hair shafts pierce the scalp surface.
- Months 6 to 8: Hair shafts thicken, gain natural pigmentation, and provide noticeable visual coverage, representing approximately 50% to 60% of expected total density.
- Months 9 to 12: Regrown hairs reach their mature calibre, texture, and wave. Hair styling becomes straightforward, and the definitive outcome of the restoration is established. For procedures involving the crown (vertex), full maturation may extend up to 14 to 15 months due to lower baseline blood flow in that region.
Patients can travel on commercial flights within 48 to 72 hours following their in-clinic evaluation. While travelling, protect the head from direct sunlight and contact with overhead luggage bins using a loose, structured hat that does not touch the recipient zone.
Hair Transplant Turkey Cost Factors: Verified Package Components and Inclusions
The overall investment for hair restoration in Turkey varies according to the total graft volume, the chosen technique such as sapphire FUE or DHI, and the direct hands-on involvement of the operating surgeon. Standard clinical packages typically combine the surgical intervention, local anesthesia, post-operative medications, translation support, and verified follow-up schedules, though patients should confirm all inclusions to avoid unexpected procedural surcharges.
Unlike Western clinics that predominantly charge per individual graft (often ranging from £2.50 to £5.00 / $3.00 to $6.50 per graft), Turkish healthcare providers generally use tiered or all-inclusive surgical package structures. International patients should evaluate what is covered clinically rather than choosing a provider based on cost alone.
Key factors that influence hair transplant turkey cost structures include:
- Surgical Method: DHI generally costs 20% to 30% more than sapphire FUE. The implanter pens require specialized single-use Choi needles and a larger clinical support team to load follicles during surgery.
- Surgeon Involvement Tier: A procedure where a licensed surgeon designs the hairline, performs punch extractions, and cuts recipient channels commands a higher fee than one where the doctor only conducts the initial consultation and delegates the rest of the surgery.
- Facility Type: Regulated surgical facilities within hospitals accredited by the US-based Joint Commission International (JCI) carry higher operational overheads than small independent outpatient polyclinics, reflecting their emergency infrastructure and strict sterilisation standards.
- Included Medications and Aftercare: Comprehensive packages include clinical-grade local anaesthetics approved by the Turkish Medicines and Medical Devices Agency (TİTCK), prophylactic antibiotic courses, anti-inflammatory pain medications, specialized scalp foam, and dedicated follow-up kits.
- Post-Surgical Therapies: Some packages incorporate complementary adjunctive therapies, such as Autologous Platelet-Rich Plasma (PRP) injections or low-level laser therapy (LLLT), to support immediate vascularisation.
A comprehensive package typically covers four-star or five-star hotel lodging for two to three nights, direct airport-hotel-clinic private transfers, and a multilingual patient coordinator. Patients should secure an itemised written quote prior to travel, ensuring there are no hidden fees for graft counts, local anaesthesia, or post-operative supplies.
How Much Is a Hair Transplant in Turkey?
Hair restoration packages in Turkey are provided following individualized clinical evaluations rather than uniform flat rates, reflecting graft complexity and practitioner credentials. Prospective patients receive itemized quotes directly after remote trichological assessment, covering all necessary surgical elements, specialized aftercare kits, and scheduled remote follow-up assessments over 12 months.
Transparent clinic pricing generally organizes into clear clinical tiers rather than arbitrary discounts. When evaluating international proposals, realistic price ranges at reputable, surgeon-guided facilities fall into these general benchmarks:
- Sapphire FUE Surgical Packages: Typically range between £1,800 and £3,200 (approximately $2,300 to $4,000 USD / €2,100 to €3,700 EUR) for standard restoration sessions up to 3,500 grafts.
- DHI Surgical Packages: Typically range between £2,200 and £3,800 (approximately $2,800 to $4,800 USD / €2,500 to €4,400 EUR), reflecting extended operating durations and consumable instrument requirements.
- Surgeon-Exclusive or Low-Density Repair Sessions: In selective practices where the primary physician performs 100% of the extraction and placement steps, pricing may follow per-graft models ranging from £1.20 to £2.50 ($1.50 to $3.20 USD) per graft, bringing total investments closer to £4,000 to £6,000.
Clinics offering complete procedures below £1,300 ($1,600 USD) often offset their costs by operating high-volume assembly lines, reducing physician involvement, and reusing disposable micro-punches. Transparent quotations should clearly state the target graft count, confirm the primary surgeon's roles in writing, itemize included post-operative care items, and avoid vague "unlimited graft" marketing terms.
Clinical Risks, Complications, and Safe Follow-Up Care
While modern follicular extraction carries low rates of severe systemic complications, prospective patients face measurable surgical risks including recipient infection, folliculitis, localized necrosis from excessive adrenaline, and telogen effluvium.
Undergoing surgery in an outpatient setting still requires careful wound management and clear follow-up protocols. The overall complication rate remains under 2% to 3% when procedures are performed in accredited, sterile environments, but prospective patients must be aware of potential adverse outcomes:
- Localised Recipient Infection: Surface bacterial infections (such as staphylococcal folliculitis) occur in less than 1% of cases with proper hygiene. Symptoms include spreading redness, increased heat, throbbing pain, and localized pustules around grafts between days three and seven.
- Skin Necrosis: A rare but severe complication caused by excessive local anaesthetic with adrenaline, dense packing (placing grafts too close together), or deep channel incisions that sever dermal blood vessels. This can result in tissue death, leaving localized scarring without hair growth.
- Folliculitis During Regrowth: Small, superficial pustules frequently appear around months three to five as new hair shafts push through the epidermis. While most resolve with warm compresses and topical antiseptic washes, extensive or painful outbreaks may require topical or oral antibiotics.
- Donor Area Overharvesting and Hypo-pigmentation: Aggressive harvesting leaves visible micro-scarring, patchy thinning, and permanent donor depletion.
- Temporary Paresthesia: Numbness, tingling, or diminished scalp sensation commonly occurs across both donor and recipient sites due to transection of superficial sensory nerve endings. This typically resolves on its own over three to six months.
- Suboptimal Graft Survival: Inadequate handling, thermal stress, dehydration during sorting, or rough placement can reduce graft survival, yielding sparse or patchy results.
Key warning signs that require urgent clinical attention include:
- Spreading redness or skin warmth extending beyond the immediate recipient or donor zones.
- Progressive, asymmetrical swelling affecting the eyelids, midface, or neck.
- Severe or escalating pain that fails to respond to prescribed oral analgesia.
- Purulent, foul-smelling exudate from donor puncture sites or recipient channels.
- Dark, purplish, or blackening patches of skin indicating compromised microvascular perfusion.
If warning signs appear, contact your clinic's medical team immediately and consult a local general practitioner or emergency department. Do not delay seeking medical assessment for spreading skin infections or potential tissue necrosis in order to arrange international travel.
Frequently Asked Questions
When can I resume exercise and standard physical routines after surgery?
Light walking can resume on day three post-procedure, but avoid cardiovascular exercise, weightlifting, and activities causing heavy sweating for at least 14 days. Intense contact sports, swimming in chlorinated pools or open salt water, and wearing tight motorcycle or sports helmets should be avoided for a full four weeks to prevent friction, graft dislodgement, and microbial infection.
Will I require a second hair transplant in the future?
A hair transplant does not stop the natural progression of genetic hair loss in untreated native follicles. While transplanted hairs from the occipital zone remain resistant to DHT, untreated native hair around the transplant may continue to thin over time. Patients with early-stage balding or strong genetic predispositions may choose a secondary touch-up session years later, provided their remaining donor capacity allows it.
Can transplanted hair fall out years after the procedure?
Transplanted hairs retain the biological characteristics of the occipital donor zone, providing long-lasting coverage for most patients. However, age-related thinning, natural hormonal shifts, and conditions such as senescent alopecia can gradually decrease hair shaft diameter and visual density over several decades.
How should international patients sleep during the initial recovery week?
Sleep on your back with your head and neck elevated at a 45-degree angle using an ergonomic neck pillow for the first seven nights. This position prevents the recipient area from rubbing against pillows and helps lymphatic drainage, which reduces post-operative forehead and facial swelling. Avoid rolling onto your stomach or sides until the clinical wash at day 10 confirms the grafts are securely anchored.
Not sure which hospital is right for your case?
Upload your medical reports and our AI will match them against the verified capabilities of every hospital in our network.
- Upload your reports (no account needed)
- Our AI matches your case with hospitals that can actually treat it
- You choose who receives your case. We present it in the hospital’s own language, and the hospital replies directly to you
Free and anonymous. Your documents stay private until you decide to send them.


