
Vitamin K Shots for Newborns: Preventing Deficiency Bleeding and Protecting Infant Health

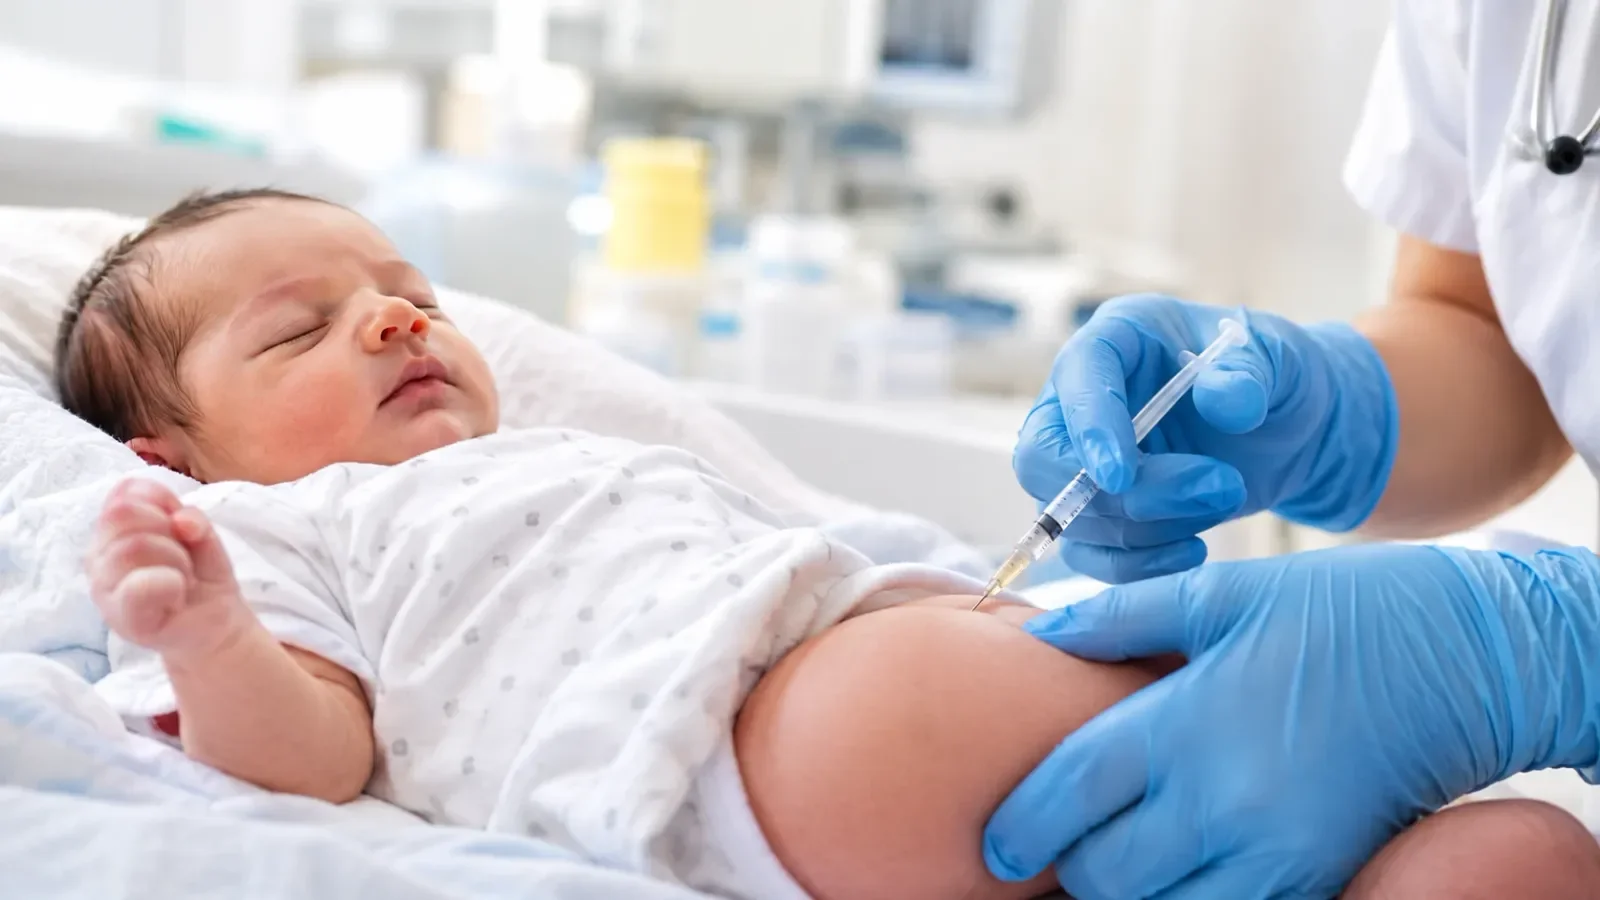
Quick Answer: The vitamin K shot provides essential clotting factor support that newborns cannot produce naturally, protecting infants from severe internal and intracranial bleeding throughout their first six months of life. Administered as a single intramuscular injection shortly after birth, it bridges a universal neonatal physiological deficit until dietary intake and gut bacteria establish independent vitamin production.
Key Takeaways:
- Every newborn is born with low physiological reserves of vitamin K due to poor placental transfer, an immature gut microbiome, and minimal concentrations in human breast milk.
- Without supplementation, infants face a heightened risk of vitamin K deficiency bleeding, an unpredictable condition that can trigger catastrophic brain hemorrhage.
- Recent public health reports indicate a notable increase in documented cases of neonatal deficiency bleeding, underscoring the importance of prophylaxis.
- The standard prophylactic injection contains synthetic vitamin K1 (phylloquinone) and creates a gradual-release depot in the thigh muscle, maintaining steady clotting factor levels for months.
- Multi-dose oral vitamin K regimens offer partial protection against early bleeding but demonstrate significantly higher failure rates against late-onset intracranial hemorrhage compared to the intramuscular shot.
Vitamin K deficiency bleeding in neonates is a serious hematologic condition characterized by spontaneous, severe bleeding caused by an inadequate supply of vitamin K-dependent clotting factors (Factors II, VII, IX, and X). Because human infants cannot manufacture or store adequate amounts of this fat-soluble micronutrient prior to birth, medical professionals since the early 1960s have recommended universal prophylactic administration of phylloquinone to every newborn within hours of delivery.
Understanding Vitamin K Deficiency Bleeding (VKDB) and Recent Increases
Vitamin K deficiency bleeding (VKDB) is a rare but life-threatening coagulopathy where insufficient vitamin K impairs clotting factor activation, leading to sudden, severe hemorrhage in previously healthy infants. Recent November 2026 observational studies across 11 million infants published in JAMA Pediatrics documented an increase from 189 cases in 2017 to 1,764 cases in 2025, driven primarily by rising injection refusal rates.
The biological cascade underlying vitamin K deficiency bleeding hinges on the post-translational modification of blood coagulation factors. Vitamin K serves as an indispensable cofactor for the enzyme gamma-glutamyl carboxylase. This enzyme converts specific glutamic acid residues into gamma-carboxyglutamic acid within Factors II (prothrombin), VII, IX, and X, as well as regulatory proteins C and S. Without adequate carboxylated residues, these clotting factors cannot bind calcium or interact with phospholipid membranes on activated platelet surfaces, bringing the normal coagulation cascade to an abrupt halt.
When an infant lacks adequate active clotting factors, routine minor vascular insults from normal neonatal movement, standard handling, or birth trauma fail to seal. The resulting hemorrhage can occur invisibly inside internal organs or within the central nervous system. Before universal injection protocols were established, classical and late hemorrhagic disease affected an estimated 0.25% to 1.7% of all births, leaving hundreds of infants with severe motor disabilities or resulting in fatality.
The sharp upward trajectory in reported cases through 2025 reflects shifting parental vaccination perceptions spilling over into routine neonatal interventions. Because the vitamin K injection is frequently administered alongside or immediately following delivery room care, some parents mistake this nutritional therapy for an immunizing vaccine or assume that an unmedicated, physiological birth eliminates the need for pharmaceutical supplementation. Pediatric surveillance highlights that this surge occurred almost exclusively among infants whose parents opted out of intramuscular prophylaxis at birth.
Why Newborns Naturally Lack Vitamin K at Birth
Every newborn is born functionally deficient in vitamin K because the molecule transfers poorly across the human placenta, fetal liver storage remains minimal, and a newborn infant's gut flora cannot yet synthesize the vitamin. In addition, mature human breast milk contains low concentrations of vitamin K (typically 1 to 4 micrograms per liter), making unsupplemented breastfed infants particularly vulnerable to late-onset deficiency.
The human placenta operates as an active, selective barrier between maternal and fetal circulations. While water-soluble vitamins traverse this barrier relatively unhindered through specialized transport mechanisms, fat-soluble molecules, particularly phylloquinone (vitamin K1), cross with profound inefficiency. Umbilical cord blood measurements routinely indicate that fetal plasma vitamin K concentrations are less than one-fiftieth of maternal plasma levels, even when maternal blood concentrations are entirely normal. Maternal dietary supplementation during late pregnancy increases maternal serum levels but fails to elevate fetal cord blood reserves to clinically protective thresholds.
Furthermore, fetal and neonatal hepatic tissue maintains minimal storage capacity for the vitamin. Adults store several weeks of functional fat-soluble reserves in liver tissue and recover substantial amounts through an endogenous recycling pathway known as the vitamin K epoxide cycle. Neonatal hepatic tissue exhibits low baseline levels of epoxide reductase activity, leaving the infant reliant on external intake rather than internal cellular recycling.
In adults and older children, intestinal microflora, specifically Bacteroides, Enterobacter, and various Escherichia coli strains, synthesize menaquinones (vitamin K2) within the lower gastrointestinal tract, which can be absorbed to support baseline coagulation. A newborn infant enters the world with an essentially sterile or low-colonization gut. It takes several weeks to months for an infant's intestinal tract to cultivate an established microbial ecology capable of producing measurable menaquinones.
Dietary intake during the exclusive milk-feeding window provides little compensation for breastfed infants:
- Mature human breast milk delivers approximately 1 to 4 micrograms of phylloquinone per liter.
- An average breastfed infant consuming 750 milliliters of milk per day receives fewer than 3 micrograms of daily vitamin K, falling well short of the recommended intake needed to correct newborn coagulation deficits.
- Commercial infant formulas are fortified according to regulatory standards (mandated by the US FDA in the United States and the European Commission in the European Union), delivering between 50 and 100 micrograms per liter, which protects formula-fed infants from late-onset deficiency after the first weeks of feeding.
- Exclusively breastfed infants who do not receive prophylactic vitamin K at birth experience progressive depletion of their initial reserves, reaching their most vulnerable state between 2 and 12 weeks of life.
Early, Classical, and Late VKDB: Timeline and Critical Warning Signs
VKDB presents in three distinct clinical windows: early-onset occurs within 24 hours of delivery, classical VKDB emerges between days 2 and 7, and late-onset strikes between 2 and 12 weeks of life, predominantly affecting exclusively breastfed babies. Warning signs include unexplained bruising, oozing from the umbilical cord or circumcision site, pale skin, blood in the stool or urine, persistent vomiting, and neurological signs such as lethargy or seizures indicating intracranial bleeding.
The clinical manifestations of this coagulopathy differ significantly depending on the timing of onset and the infant's feeding regimen.
| Form of VKDB | Usual Onset | Primary Risk Factors | Common Bleeding Sites | Frequency Without Prophylaxis | Intracranial Bleeding Risk |
|---|---|---|---|---|---|
| Early-Onset | Birth to 24 hours | Maternal medications (anticonvulsants, cephalosporins, warfarin, rifampin) | Cephalohematoma, intrathoracic, intra-abdominal, gastrointestinal | Reported up to 12% among at-risk drug exposures | Moderate |
| Classical | 2 to 7 days | Delayed or inadequate milk intake, no injection at birth | Umbilical stump, circumcision site, gastrointestinal tract, skin puncture sites | 0.25% to 1.5% of unsupplemented births | Low to Moderate (~10% of cases) |
| Late-Onset | 2 to 12 weeks (up to 6 months) | Exclusive breastfeeding, no injection at birth, underlying cholestasis or malabsorption | Central nervous system (subdural, subarachnoid, intracerebral), skin, gut | 4.4 to 10.5 per 100,000 unsupplemented births | Extremely High (50% to 65% of cases) |
Early-onset disease typically occurs when maternal pharmaceutical compounds taken during pregnancy accelerate fetal degradation of vitamin K or directly antagonize clotting factor synthesis. Antiepileptic drugs such as carbamazepine, phenytoin, and phenobarbital, as well as certain antitubercular medications, induce fetal hepatic cytochrome P450 enzymes that deplete already fragile fetal stores. Bleeding in this window is often massive and presents within hours of delivery.
Classical VKDB manifests toward the end of the baby's first week. During this phase, early colostrum intake is low in overall volume, maternal milk transition is underway, and systemic stores are exhausted. Bleeding commonly originates from minor trauma sites: the umbilical cord separation margin, a neonatal circumcision, or heel-stick sampling points. Gastrointestinal hemorrhage presenting as blood in emesis or stool is another frequent presentation.
Late-onset VKDB carries the gravest clinical prognosis. Occurring when parents assume their baby is past the vulnerable newborn stage, this form strikes infants who appear healthy, thriving, and gaining weight normally on an exclusive breast milk diet. More than half of infants with late VKDB suffer sudden intracranial hemorrhage.
Warning signs that demand immediate emergency pediatric evaluation include:
- Unprovoked cutaneous bruising, particularly across the forehead, torso, or extremities.
- Persistent capillary oozing from the umbilical stump or skin prick sites that lasts longer than several minutes.
- Mucosal bleeding, including petechiae inside the mouth or spontaneous nosebleeds.
- Frank bright red blood or black, tarry material (melena) appearing in bowel movements.
- Pale, waxy skin coloration paired with unexplained rapid heart rate.
- Neurological changes: sudden somnolence, inability to arouse for feedings, a tense or bulging anterior fontanelle, irregular breathing, high-pitched inconsolable crying, or rhythmic twitching and seizures.
The Newborn Vitamin K Injection: What It Contains and How It Works
Routinely administered within six hours of birth since 1961, the intramuscular injection delivers phylloquinone (vitamin K1) directly into the baby's thigh muscle (vastus lateralis), creating a slow-release depot that sustains clotting factors until dietary intake stabilizes. Modern pediatric formulations contain synthetic vitamin K1 along with safe solubilizing agents (such as polyoxyethylated fatty acid derivatives and propylene glycol) and buffers, with preservative-free pediatric preparations widely available to avoid benzyl alcohol exposure.
Understanding the pharmacokinetics of the injection clarifies why a single dose provides months of clinical protection. Phylloquinone is highly lipophilic and insoluble in water. When delivered into the vascularized tissue of the vastus lateralis, the lipid-formulated medication forms a microscopic reservoir within the muscular interstitium.
Over the subsequent weeks and months, small fractions of phylloquinone steadily diffuse into the infant's microcirculation, providing continuous precursor material for hepatic gamma-glutamyl carboxylase. This slow release sustains therapeutic plasma levels well past the 12-week danger zone, effectively shielding the child until weaning introduces solid foods rich in phylloquinone (such as leafy green vegetables and vegetable oils).
The standard vitamin k dose for newborn prophylaxis is standardized based on birth weight:
- Full-term neonates weighing more than 1,500 grams receive a single intramuscular injection of 1.0 milligram (0.5 milliliters of standard 2 mg/mL formulation).
- Preterm infants weighing 1,500 grams or less receive a weight-adjusted dose of 0.3 to 0.5 milligrams per kilogram to avoid excessive hepatic drug loading.
Regarding the ingredients in the vitamin k shot, formulations in the United States and international markets are tailored specifically to pediatric safety:
- Active ingredient: Synthetic phylloquinone (vitamin K1), chemically identical to the naturally occurring isomer found in plants.
- Solubilizing agents: Because pure vitamin K1 is an oil, it requires an emulsifier to stay in an injectable aqueous suspension. Formulations use polyoxyethylated fatty acid derivatives (such as polysorbate 80) or polyethoxylated castor oil derivatives in minute quantities.
- Buffering and stabilizing agents: Anhydrous citric acid and sodium citrate dihydrate maintain a physiological pH (around 5.5 to 7.0) to prevent tissue irritation, alongside propylene glycol as a stabilizing cosolvent.
- Preservative status: Historically, multi-dose vials contained benzyl alcohol as an antimicrobial preservative. Following concerns over neonatal toxicity from benzyl alcohol in the 1980s, regulatory authorities including the US FDA and the UK MHRA mandated single-dose, preservative-free ampules and pre-filled syringes for neonatal prophylaxis, removing benzyl alcohol from standard delivery-room products.
Vitamin K Shot at Birth Pros and Cons: Benefits vs Safety Myths
Clinical evidence demonstrates that the newborn vitamin K injection significantly reduces the risk of severe bleeding, substantially lowering the risk of irreversible neurological injury and death with a single dose. Minor transient side effects are limited to localized redness, mild swelling, or momentary discomfort at the injection site, while comprehensive multidecade cohort studies have thoroughly disproven the 1990s hypothesis linking intramuscular vitamin K to childhood leukemia.
Evaluating the vitamin k shot at birth pros and cons involves comparing documented, life-saving clinical outcomes against transient procedural discomfort and unsubstantiated historical theories.
Expected clinical benefits of prophylaxis include:
- Substantial protection against classical and late-onset VKDB.
- Marked reduction in the risk of severe or disabling intracranial hemorrhage.
- Reliable hemostatic coverage for routine neonatal procedures such as circumcision.
- Maintenance of normal coagulation status during early exclusive breastfeeding.
The primary clinical advantage is protection against an otherwise unpredictable, life-threatening crisis. Clinical data demonstrate that the single intramuscular injection virtually eliminates classical VKDB and reduces the incidence of late VKDB from roughly 5 to 10 cases per 100,000 unsupplemented breastfed infants down to near zero. Among infants who suffer late-onset intracranial bleeding, reported mortality rates reach approximately 20%, and over 40% of survivors sustain lifelong neurologic deficits, including cerebral palsy, intellectual impairment, or intractable seizure disorders. A single 1-milligram shot effectively prevents the vast majority of these complications.
Concerns regarding vitamin k for newborn side effects generally center on injection site reactions and historical claims:
- Local site tenderness: Mild erythema, transient induration, or minor soreness in the vastus lateralis muscle occurs in a small percentage of infants. These localized signs typically resolve spontaneously within 24 to 48 hours without therapeutic intervention.
- Procedural distress: The mechanical puncture causes brief crying. Evidence-based comfort measures, such as immediate breastfeeding during the injection, kangaroo skin-to-skin contact with the mother, or small oral doses of 24% sucrose solution, significantly reduce infant behavioral distress scores during administration.
- Anaphylaxis: Systemic hypersensitivity reactions in neonates are extraordinarily rare, with estimated rates well under one per several million doses, typically linked to rapid intravenous administration rather than intramuscular delivery.
A persistent point of maternal anxiety stems from a 1990 British observational study by Golding et al., which suggested an association between intramuscular vitamin K and childhood leukemia. The publication prompted immediate, extensive investigation by public health bodies globally:
- Large-scale epidemiological studies conducted across the United States, the United Kingdom, Sweden, Denmark, and Germany, encompassing millions of children over multiple decades, failed to demonstrate any correlation between vitamin K injection and childhood leukemia or other pediatric malignancies.
- Systematic reviews by the American Academy of Pediatrics (AAP) and the World Health Organization (WHO) confirmed that the original study's findings represented a statistical anomaly linked to small sample sizes and control-group selection bias.
- Clinical consensus worldwide affirms that the intramuscular injection carries no established carcinogenic risk.
Oral Vitamin K vs the Shot: Is Oral Supplementation Sufficient?
Oral vitamin K drops provide partial protection against early and classical bleeding but fail to achieve the consistent bioavailable depot required to prevent late-onset VKDB reliably. Studies show that oral regimens require multiple, strict doses spanning 12 weeks, carry higher real-world failure rates due to missed doses or infant regurgitation, and currently lack widespread regulatory clearance as standard single-dose alternatives in the US and UK.
When parents hesitate to authorize an injection, they frequently ask whether oral liquid drops provide an equivalent substitute. While oral absorption across the intestinal mucosa is possible, the physiological and pharmacokinetic differences between oral administration and intramuscular depot delivery are substantial.
Oral phylloquinone produces a rapid, sharp spike in serum concentrations followed by swift hepatic clearance and biliary excretion within 24 to 48 hours. Because oral administration does not deposit a muscular reservoir, a single oral dose given at birth offers zero protection against late-onset disease at 4, 8, or 12 weeks of life.
To compensate for this rapid elimination, countries that permit oral protocols (such as the Netherlands, Germany, and Switzerland) mandate intensive, multi-dose regimens:
- Initial dose: 2.0 milligrams orally at first feeding.
- Second dose: 2.0 milligrams orally between day 4 and day 7.
- Third dose: 2.0 milligrams orally at 4 to 6 weeks of age (or ongoing daily drops of 150 micrograms from week 1 through week 12 for exclusively breastfed infants).
Despite theoretical efficacy under strict protocol conditions, real-world comparative registry studies highlight clear shortcomings of oral pathways:
- Compliance challenges: Up to 15% to 20% of families fail to complete multi-week oral regimens due to missed appointments, misplaced drops, or misunderstanding schedule complexities.
- Epithelial and digestive loss: A significant portion of an oral dose can be lost if an infant regurgitates, spits up, or experiences mild neonatal diarrhea shortly after administration.
- Occult hepatobiliary disorders: Infants with undiagnosed biliary atresia, alpha-1 antitrypsin deficiency, or neonatal hepatitis cannot absorb fat-soluble oral vitamins from the gut due to deficient intraluminal bile salts. In these infants, oral drops fail entirely, leaving them exposed to late-onset intracranial hemorrhage despite full parental compliance. The intramuscular shot bypasses the biliary digestive system completely, providing reliable absorption even in the presence of cholestatic disorders.
- Regulatory absence: In the United States, the US FDA has not approved any oral formulation of vitamin K specifically licensed or standardized for neonatal prophylaxis. Products purchased online are often unregulated dietary supplements with variable potency, unverified bioactivity, and non-standardized droppers.
Frequently Asked Questions
Why give vitamin k to newborn infants instead of waiting for solid foods?
Newborn infants cannot wait until solid food introduction at six months because their clotting factor reserves are depleted within the first days of life. Without early prophylaxis, the highest risk for fatal internal bleeding occurs between the second and twelfth week, long before a baby can safely consume or digest phylloquinone-rich solid foods.
Does the vitamin K injection count as a vaccine?
The vitamin K injection is a nutritional micronutrient supplement rather than an antigenic vaccine. It contains no weakened viral particles, bacterial antigens, or immune adjuvants; its sole function is to supply a vital vitamin that the baby's liver requires to activate normal blood clotting proteins.
What should parents discuss with their pediatrician if they feel hesitant?
Parents should ask their pediatrician to walk them through the specific preservative-free formulations used at their birthing hospital, practical pain-reduction methods during administration (such as simultaneous nursing), and the comparative risk rates of VKDB. Open, non-judgmental dialogue ensures families make an informed choice based on hematological evidence rather than delivery room stress.
Can maternal diet or supplements during late pregnancy replace the shot?
High-dose maternal dietary intake or prenatal supplementation cannot replace the newborn shot because the human placenta strictly limits the transfer of fat-soluble vitamin K into fetal circulation. Even when maternal blood concentrations are high, cord blood levels remain uniformly deficient at birth.
Not sure which hospital is right for your case?
Upload your medical reports and our AI will match them against the verified capabilities of every hospital in our network.
- Upload your reports (no account needed)
- Our AI matches your case with hospitals that can actually treat it
- You choose who receives your case. We present it in the hospital's own language, and the hospital replies directly to you
Free and anonymous. Your documents stay private until you decide to send them.


